
How to take laboratory samples for TSE testing and confirmation
Sample requirements, including sample size and composition, and methods for removing the brainstem and cerebellum.
Background
The first stage of all the current TSE diagnostic or screening tests involves the sampling of the central nervous system at the level of the brainstem, and the subsequent examination of the sampled tissue for the presence of disease-specific PrP (PrPSc or PrPres).
As new, atypical, types of disease have been identified in cattle (H-BSE and L-BSE) and sheep (atypical scrapie or Nor98) it is becoming apparent that the cerebellum is also a key area for robust confirmation and classification of these variants.
PrPSc has proved to be the most consistent marker for all known forms of TSE, being present in the CNS of all clinically suspect TSE cases, and it has been shown experimentally that demonstrable accumulations of PrPSc arise in the CNS (and in a more variable way in the lymphoreticular system) in advance of vacuolation or any clinical signs. It is thus a useful marker in pre-clinical animals, as well as in those presenting with overt disease.
The brain consists of multiple interrelated but anatomically and functionally distinct areas, and PrPSc accumulation shows distinct anatomically specific tropisms which result in clear-cut patterns of PrP accumulation (figure 1). These patterns are specific both in end-stage disease, and through the pathogenesis of each form of TSE.

Specific sampling requirements
These guidelines are based on the approaches recommended in the WOAH manual chapters for BSE and scrapie:
Codes and Manuals - WOAH - World Organisation for Animal Health
The minimum sampling requirement for any animal from either source population is the brainstem (at the level of the obex). In addition, for small ruminants it is advised that part of the cerebellum is also collected. Both of these brain areas can be accessed through the foramen magnum using a proprietary sampling spoon (see below for sampling methods).
Cerebellum may also be a useful sample to assist with confirmation of the classification of atypical bovine TSE.
The quantity of tissue taken for testing should be sufficient to provide the following:
a hemisection of fresh brainstem at the level of the obex, for the initial rapid test (or a full transverse section immediately adjacent to the obex, or equivalent sample taken unilaterally using one of the commercially available sampling devices).
a fixed cross-section, or hemi-section2 of brainstem at the level of the obex for confirmatory IHC provided the degree of autolysis does not preclude fixation (Ideally this sample would be fixed immediately, but for practical reasons it is appropriate to keep the sample chilled and fix it on receipt of a positive rapid test. In some countries it is established practice to freeze material prior to fixation. While this does not detract from the subsequent immunoreactivity of positive cases, it can significantly compromise the tissue morphology, making the contextual interpretation of negative or equivocal immunostains difficult or impossible.)
a fixed section of cerebellum, or sufficient fresh cerebellum to conduct a Western blot – this may be required for the confirmation of atypical scrapie
sufficient remaining fresh-frozen medullary tissue (adjacent to the obex) and fresh-frozen cerebellum to provide fresh material for further primary molecular testing and possibly a range of secondary and tertiary testing if required (5g to 10g whenever possible)
lymphoreticular tissues when available are always an advantage as is additional tissue from other brain areas – although not essential for statutory purposes, they will be important in determining pathogenesis and infectivity of the TSE as well as characterising the TSE strain present in peripheral tissues if results differ from the expected confirmation at the level of the obex
Brainstem and cerebellum removing methods
The samples should be collected in a manner that prevents any risk of contamination between successive samples.
APHA method
Place the disarticulated head upside down on table with the foramen magnum facing the operator. Remove any blood clots obscuring the view of the brainstem and identify the dura mater. Use a clean pair of scissors to reflect the dura mater and expose the brain stem.
Gently hold the brain stem as close to the end as possible with a new/clean pair of forceps – preferable plastic ones that can be disposed of – and move the brainstem to the side to visualise the cranial nerves. Insert the scissors – preferable disposable ones – into the foramen magnum and cut through the cranial nerves (VII–XI). Do this on both sides of the brainstem, taking care not to damage it.
All subsequent manipulations are performed in the subdural space i.e. in the space between the dura matter and the brainstem.
Using the forceps, very gently pull the brainstem until it is straight and insert a plastic disposable spoon above the brainstem with the cutting edge of the spoon facing down. Keep the blade of the spoon against the bone above as it is inserted. Guide the spoon gently forward as far as it can possibly go depending on the size of the skull – approximately 8 to 10cm – taking care not to destroy the brain stem. When in position, point the cutting edge of the blade downwards by lifting the handle upwards to sever the brainstem.
Cut through the cerebellar peduncles by moving the handle from side to side.
After completing the cutting, carefully withdraw the spoon and insert it with the blade pointing downwards underneath the brainstem until it enters to a depth of approximately 8 to 10cm again depending on the size of the skull. The length of the previous insertion should be used for reference. Gently move the blade side to side and downwards, cutting through the rostral medulla (avoiding rotational movement as this will damage the obex).
Gently pull with the forceps and using the spoon as a scoop pull as much brainstem as possible out of the skull. If resistance is encountered, continue to cut through the brainstem with a side to side and downward motion of the handle.
With the head still upside down on the table, insert the spoon underneath the cerebellum, and lever it upwards into the centre of the space that was vacated by the brainstem. Move the spoon from side to side and downwards to cut parts of the cerebellum and using the spoon as a scoop remove the cerebellar section through the foramen magnum.
There are available several kinds of brain stem extraction spoons differing in shape and size (Figure 2). Shape is not so critical. Size should much the size of the skull – irrespective of species – and it should fit through the foramen magnum without destroying the brainstem.

Sampling of brainstem for screening tests
Rapid test protocols for active surveillance of healthy slaughter and/or at-risk populations generally require a specific weight of brainstem tissue, taken at the level of the obex, to be presented to the test.
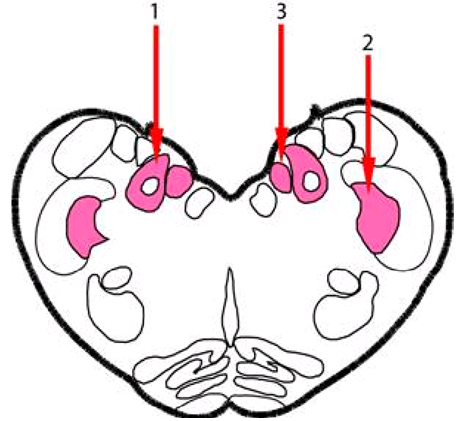
In C-BSE and classical scrapie the distribution of PrPSc appears to be highly consistent, with early changes appearing first in the dorsomedial nuclei in the brainstem at the level of the obex. Following experimental oral challenge with C-BSE, the earliest visible PrPSc accumulation is consistently seen (using immunohistochemistry (IHC)) in the nucleus of the solitary tract (figure 3, 1), with involvement of the adjacent dorsal motor nucleus of the vagus nerve (DNV, figure 3, 3) and the nucleus of the spinal tract of the trigeminal nerve (figure 3, 2) following soon after. In classical scrapie the first neuroanatomical area involved is the DNV. The IHC patterns observed in many preclinical field cases detected through surveillance support the consistent early involvement of these areas in natural disease. These areas are recognised as the diagnostic target areas for sampling (figure 3).
In advanced clinical cases, all the grey-matter areas within the brainstem become affected to some extent (figure 4).

Brain stem sampling for testing
The following approach usually requires a coronal section of obex approximately 2mm thick. The section is halved sagittally and one half is fixed whilst the other half is kept fresh. The unfixed half is sectioned with a single cut which incorporates the target areas for C-BSE and classical scrapie (figure 5). These sections can be completed with the use of a plastic catering knife instead of a scalpel to address health and safety concerns. The knife or scalpel is disposed of as clinical waste after each sample is processed to avoid cross-contamination.

In small ruminants the principal target area of classical scrapie (the dorsal nucleus of the vagus) lies very close to midline (figure 3 and 5), and any approach which relies upon hemisectioning through the midline has little tolerance for inaccuracy.
This approach may give rise to some health and safety concerns depending on the type of blade used, and it also requires that each sample is weighed and trimmed before use, which is time-consuming
This has led to the development of sampling techniques in which a graduated syringe is used to take a longitudinal ‘core’ sample of brainstem. Such equipment is sometimes offered as part of a commercial test package, and has to be evaluated as fit for purpose, in particular to ensure that any tissue disruption as a result of sampling does not compromise the suitability of material for confirmatory testing should it be required. In principle these sampling syringes take a core of grey matter from the obex region of the brainstem thereby reducing any dilution effect of the peripheral white matter and increasing the sensitivity of the test. If used correctly, and with a clear understanding of the three-dimensional anatomy of the TSE target areas these tools can perform adequately.
However, there are a number of potential drawbacks with this technique that users should be aware of and conduct appropriate monitoring checks. One potential danger with syringe-type ‘core’ extractor samples taken from variable distances caudal to the obex is that the resulting sample may potentially miss the target areas particularly if the sampling tract veers laterally or ventrally (figure 6). To avoid compromising the sensitivity of the test, the sampler must ensure that the relevant TSE target areas are adequately represented.
 Figure 6: Bovine brain stem sampled using a syringe tool to aspirate nervous tissue. The asterisks indicate sampled areas. The circles indicate the position of the nucleus of the solitary tract, the target area for C-BSE.
This presents a potential sensitivity problem, especially in active surveillance cases where the PrPSc accumulation is likely to be very focal and anatomically targeted (figure 3 and 5). Robust training and great care are needed in the application of this type of sampling method to ensure that the initial rapid test is not compromised by the collection of a sample which does not represent the desired target area.
All of the above issues apply also to small ruminants, with the added complication that PrP distribution patterns vary more than in cattle, and the physical size of the brainstem is smaller than in cattle.
Suboptimal brainstem removal and preservation
This can be a problem, especially when dealing with fallen stock, where material may be significantly autolysed before sampling takes place. In such cases, the obex region may be damaged, incomplete, or not preserved optimally (figure 7) or the sample may be so distorted or autolysed that anatomical orientation is not possible (figure 8).
In these cases, it will not be possible to take an anatomically targeted sample. This cannot be avoided, but it should be recorded, to assist with interpretation of the resulting test results, and to feed back to the personnel collecting the samples that such poor-quality samples should be avoided whenever possible.

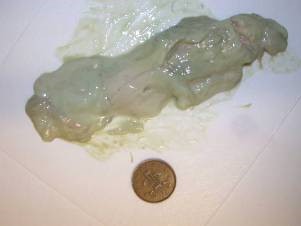
Figure 7: The obex is identifiable but the sample is incomplete (a), or the tissue integrity is compromised due to autolysis (b).


Figure 8: The brainstem is distorted due to poor sampling or severe autolysis and obex cannot be identified.
Accepting that this should be a secondary option only, where the obex is not identifiable, other parts of the brain stem/cervical spinal cord can be tested using approved rapid tests, even though their approval is currently specific to testing of the obex. In this case a positive result is valid and should be reported as such. Negative results must however be reported with the caveat that optimal tissues were not available for testing. The alternative option is to report such tissues as 'no test' i.e. un-testable as the target tissue is not available.
Action advised
Each testing laboratory should ensure that all local sampling instructions contain appropriate detailed reference to the cross-sectional and longitudinal anatomy of the structures which require to be targeted.
Additionally, instructions must be included on how to sample material, which is not optimally collected, orientated or properly identifiable at an anatomical level when it is not possible to correctly position the sampling tool, or accurately identify the obex.
It is advised that the accuracy of sampling is monitored by the testing laboratory by review of a randomly selected proportion of negative cases in addition to any positives which are referred for confirmation.